The tumour was removed without a plan and pathology showed sarcoma: what next?
This situation needs a structured reassessment, not a rushed repeat operation. The goal is to reconstruct the diagnostic and surgical picture before choosing the next step.
What is an unplanned excision?
It means a soft-tissue tumour was removed without an oncological work-up, appropriate imaging, planned biopsy and pre-defined surgical margins - often because sarcoma was not suspected before surgery.
The problem is not only an R1 margin. The incision, dissection plane, haematoma or seroma can enlarge the anatomical field that has to be considered during definitive treatment and may make reconstruction more complex.
What ideally should have happened before the first excision
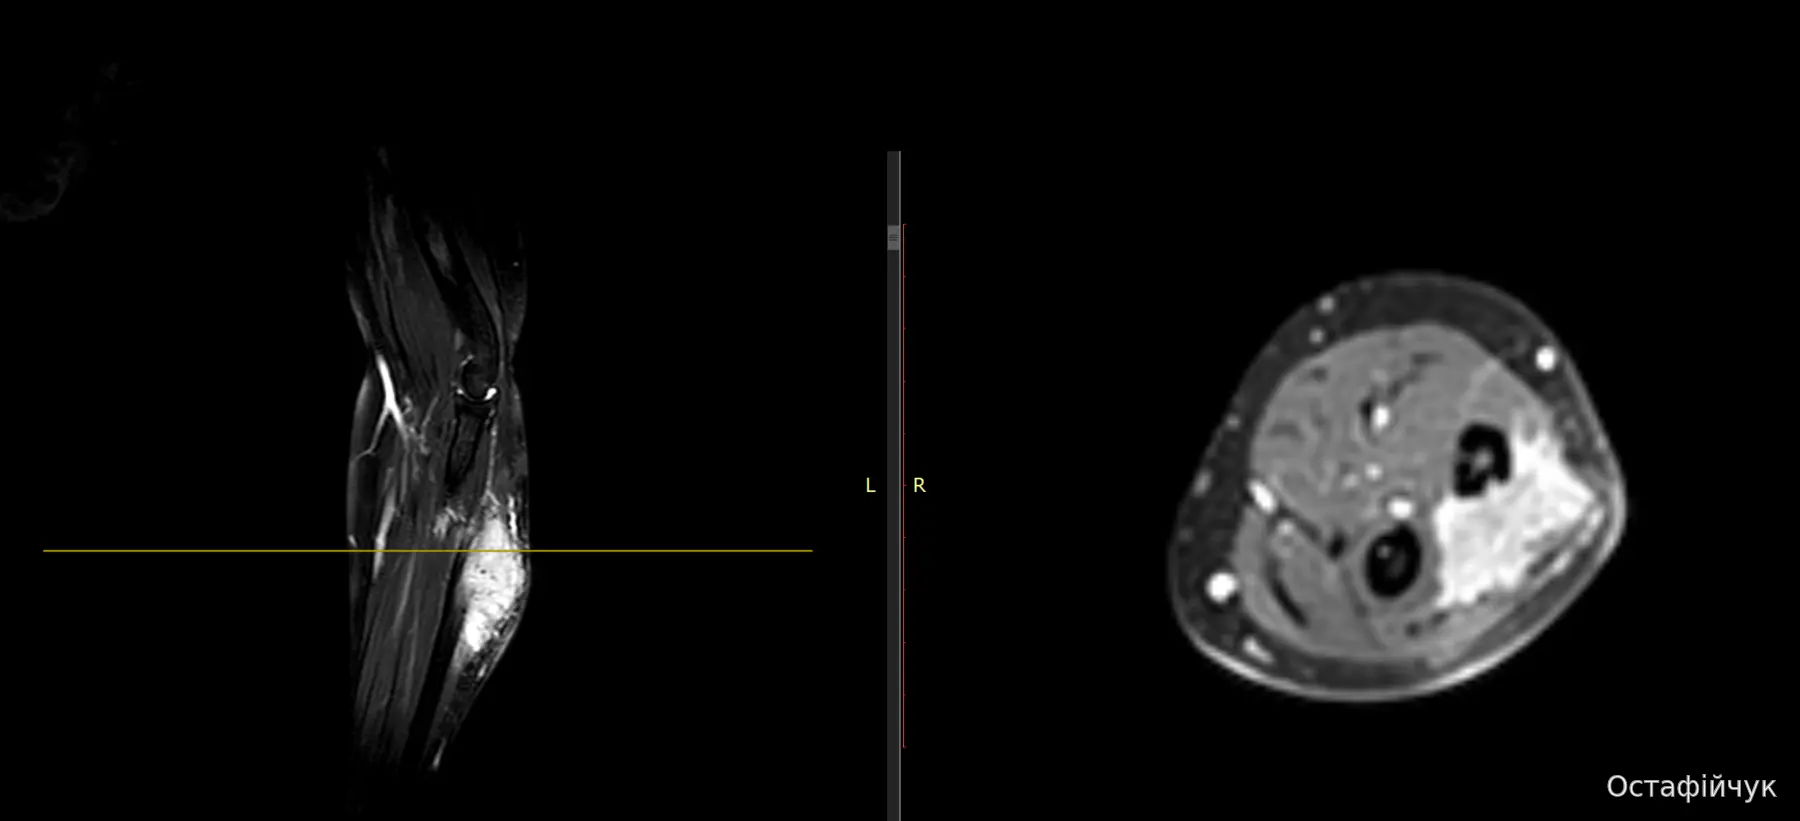
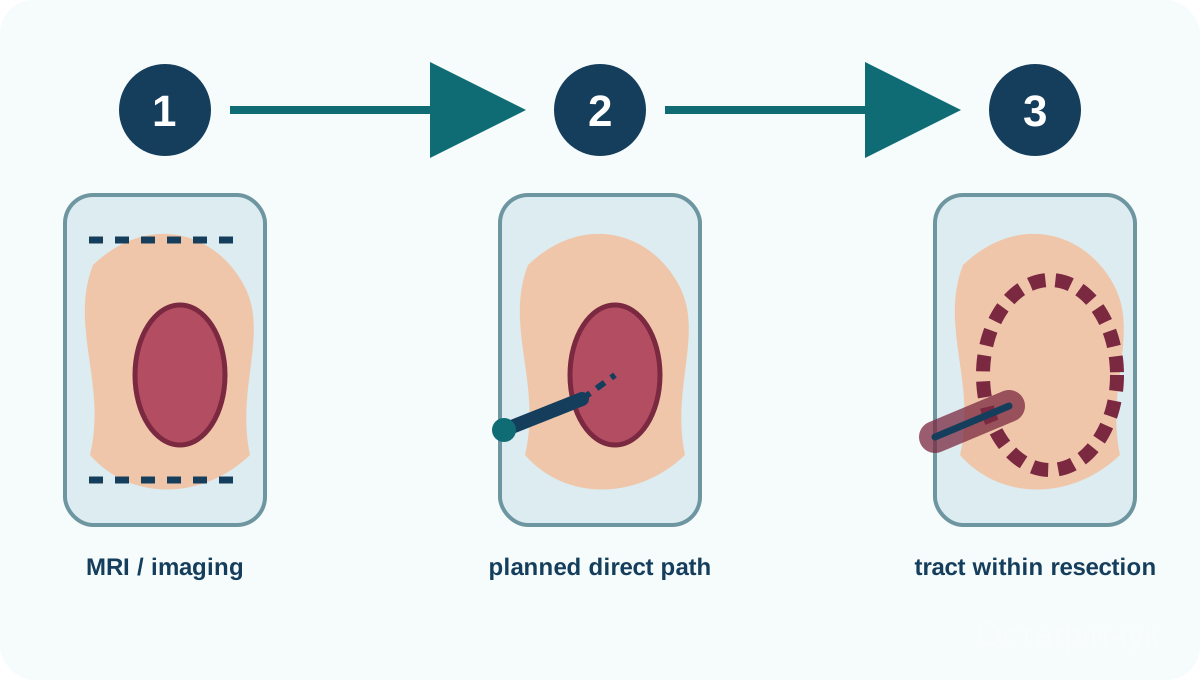
Reconstruct the entire case before re-operating
- obtain the original pathology report;
- retrieve slides and paraffin blocks for expert review;
- obtain the operative note and exact incision information;
- collect prior ultrasound, MRI, CT and DICOM files;
- clarify whether margins were R0, R1, R2 or simply unknown;
- plan postoperative MRI with awareness of the time elapsed since surgery.
Why postoperative MRI has limitations
MRI helps define the operative bed, previous dissection planes and suspicious areas, but oedema, bleeding, seroma and scar can mimic residual tumour. Imaging must be interpreted together with pathology and the operative history.
Why pathology review matters
Sarcoma is highly heterogeneous. Some diagnoses can be established with morphology and IHC; others require FISH, RT-PCR or NGS. Modern guidance supports expert review before definitive treatment when the diagnosis was made outside a specialist network or remains uncertain.
Is re-excision always required?
No, but it is frequently discussed. When margins are positive or uncertain and a meaningful oncological margin can be achieved with acceptable morbidity, re-excision of the prior operative field remains a standard component of management. The decision depends on subtype, anatomy, MRI findings, previous surgical contamination and reconstructive options.
What may be needed
- wider re-excision;
- reconstruction;
- radiotherapy;
- systemic therapy in selected high-risk or subtype-specific situations;
- risk-adapted follow-up.
What is not automatic
- amputation;
- chemotherapy for everyone;
- PET/CT for everyone;
- immediate repeat surgery without restaging;
- a final plan based on the word R1 alone.
Does an unplanned excision automatically mean a worse prognosis?
It worsens the local situation, but it does not automatically mean that curative treatment has been lost. In a meta-analysis of 16,946 patients, unplanned excision was associated with a higher 5-year local-recurrence risk (RR 1.35), while residual tumour found at re-excision was associated with a still higher local-recurrence risk (RR 2.59). Unplanned excision itself was not associated with statistically worse 5-year overall survival.
National Standard No.1434 supports specialist assessment, adequate imaging, morphological confirmation and MDT planning before definitive treatment. After an unplanned operation, these principles become even more important because the team must reconstruct what was done and define the true treatment field.
Evidence base
The pathway starts before surgery
After an unplanned excision, the priority is to restore a specialist pathway: expert pathology review, MRI of the bed, staging and MDT review before further surgery.
GEIS 2018 reported 3-year overall survival of 82% in reference centers vs 70.4% in local hospitals. NETSARC 2019 found surgery in a reference center independently associated with better overall survival (HR 0.681). These are observational data, not randomized comparisons. GEIS · NETSARC.