Desmoid fibromatosis: is treatment always necessary?
Desmoid fibromatosis can infiltrate local tissues and cause significant problems, but it does not metastasise like a conventional malignant sarcoma. For many patients, modern care begins with active surveillance.
What desmoid fibromatosis is
Desmoid-type fibromatosis is a monoclonal fibroblastic tumour with locally infiltrative growth and a tendency to recur locally. It does not have metastatic potential, so it should not be presented as a conventional malignant sarcoma.
What desmoid tumour can look like under the microscope
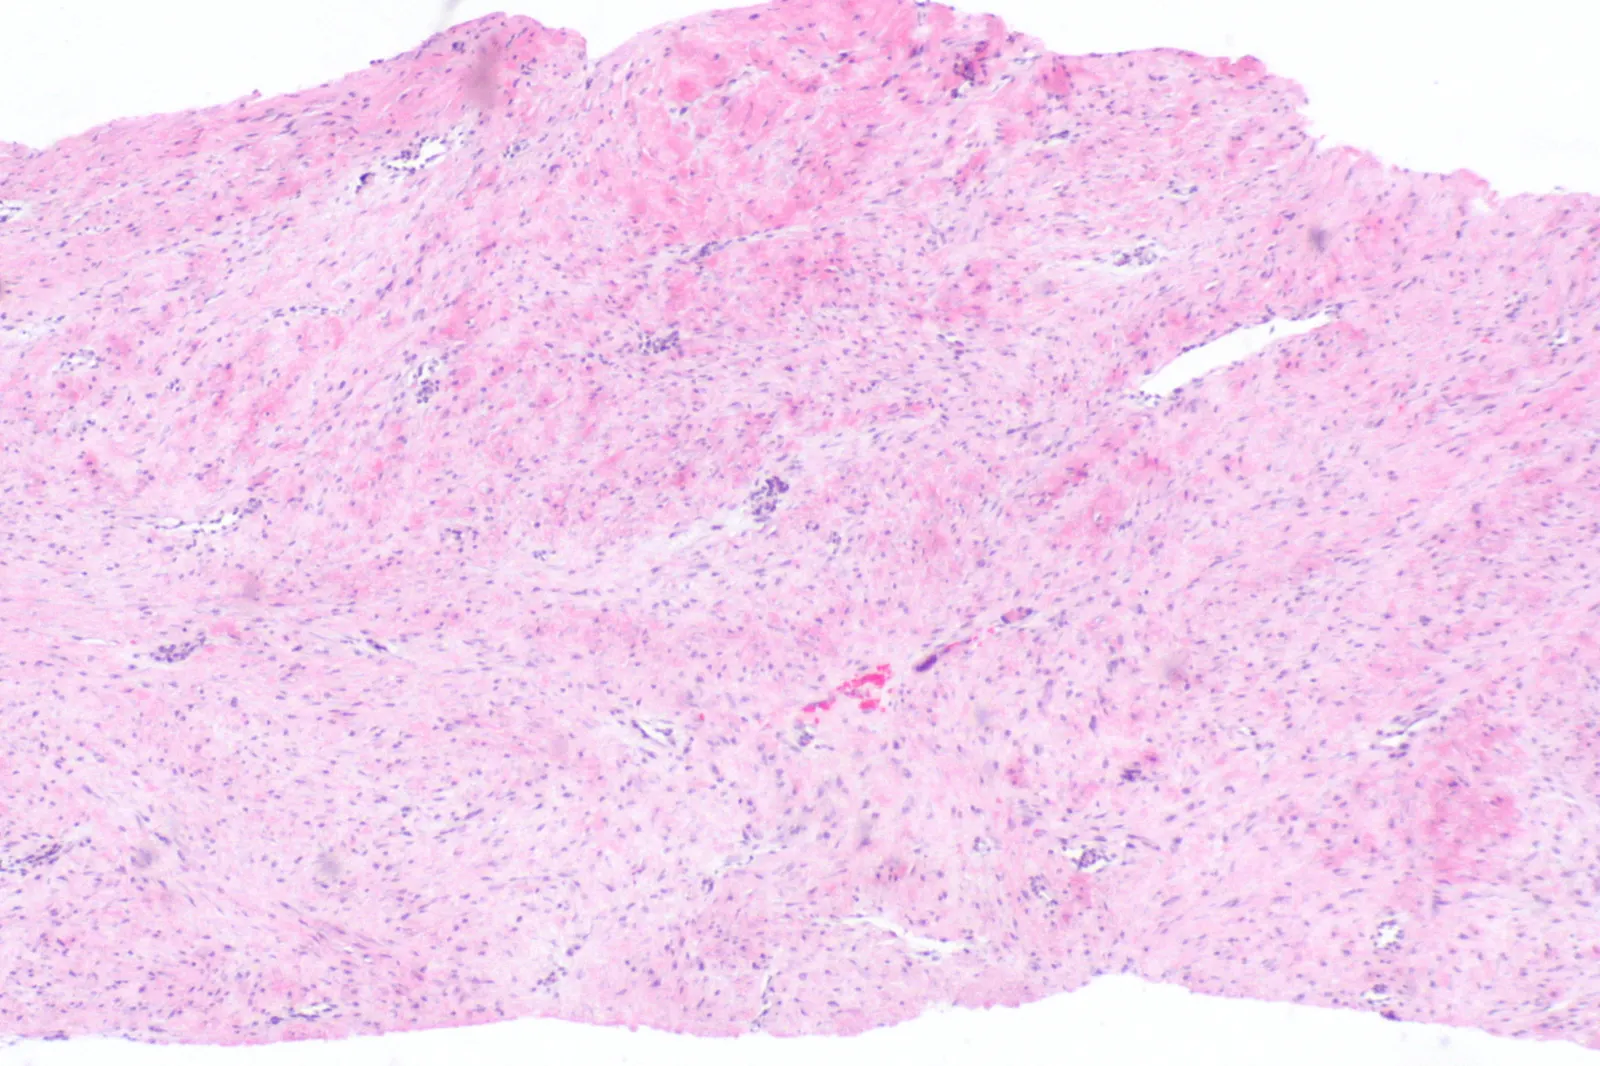
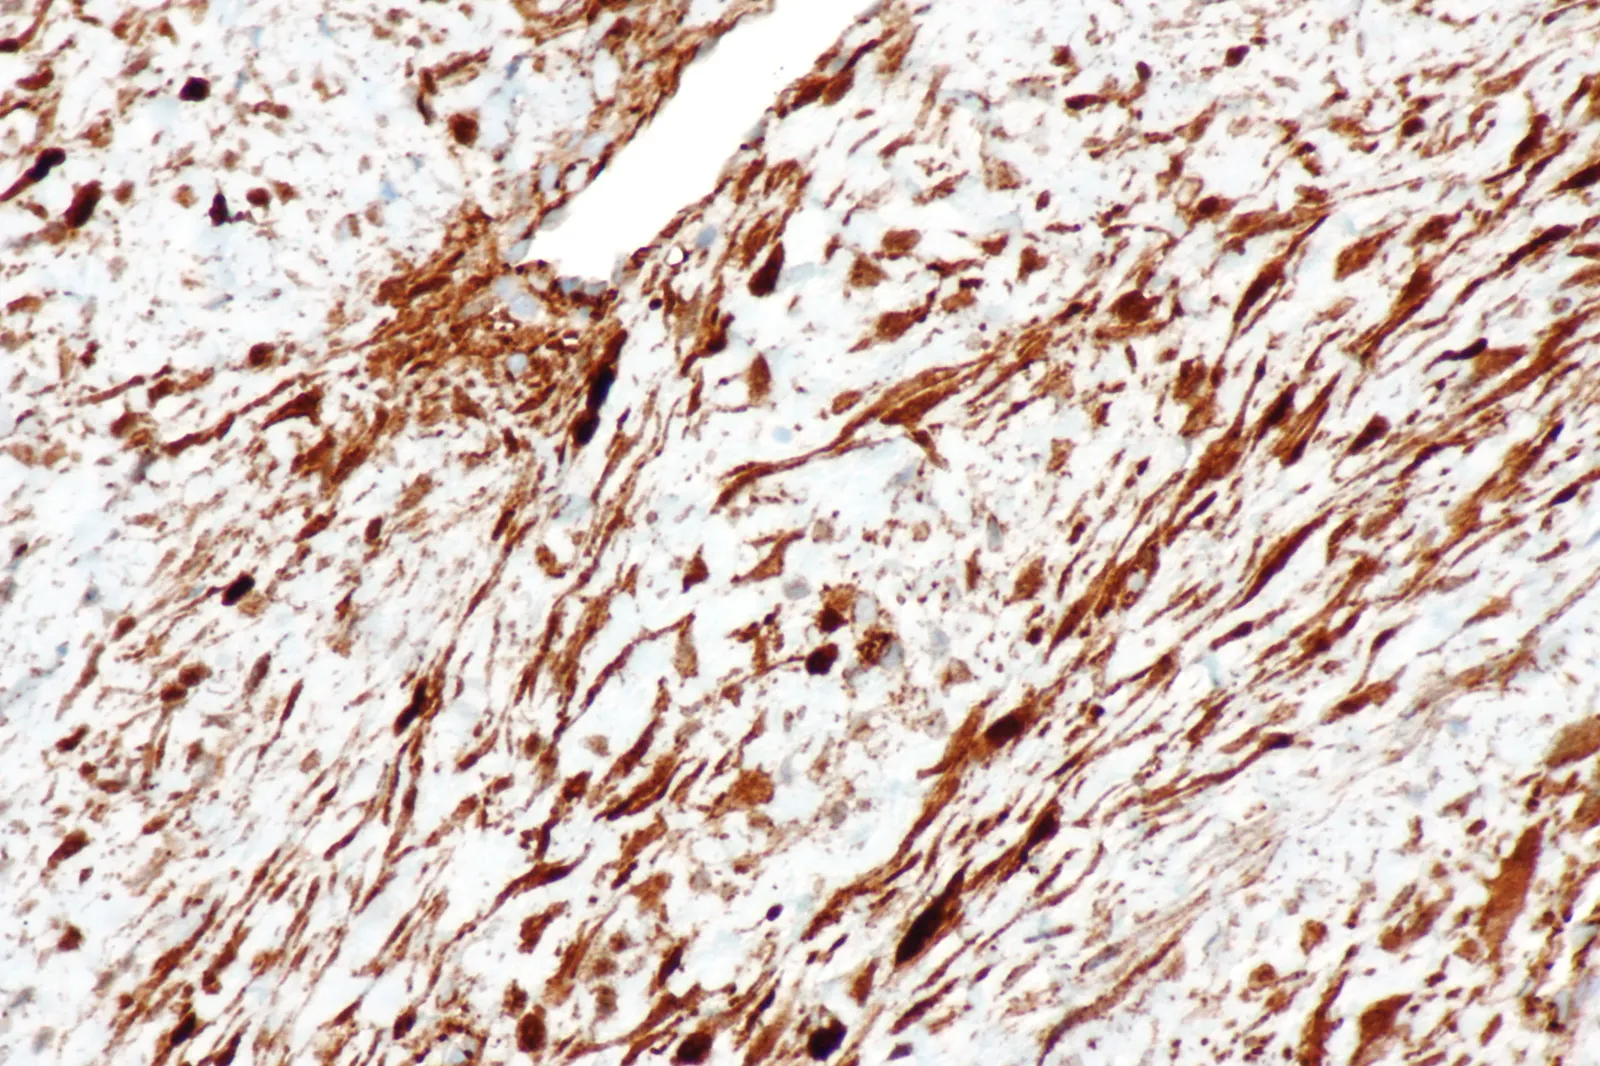
Why immediate surgery is no longer routine
The natural history is variable: some tumours stabilise and some regress without active treatment. Up-front surgery can therefore create avoidable morbidity, particularly when resection would require major reconstruction.
Active surveillance
A common first approach for asymptomatic patients without threat to an organ or function. Monitoring combines symptoms and serial MRI/CT depending on the site.
Active treatment
Considered for documented persistent growth, pain or other symptoms, functional compromise, compression of critical structures or anatomy where further growth would substantially reduce treatment options.
How often imaging is repeated
Early reassessment is often performed after approximately 8-12 weeks, then intervals can be lengthened when the disease is stable. One MRI shows anatomy; serial imaging shows behaviour.
When surgery can still be reasonable
Surgery remains appropriate in selected progressing tumours when resection can be achieved with acceptable functional and cosmetic morbidity. Modern recommendations particularly recognise selected anterior abdominal-wall tumours as a setting where resection can be reasonable.
Systemic treatment options
When treatment is required, the choice depends on progression rate, symptoms, age, site, reproductive plans and access. Current options include nirogacestat, sorafenib, pazopanib, imatinib and chemotherapy in selected settings.
Nirogacestat
In the randomised DeFi study, the risk of progression or death was reduced by about 71% versus placebo (HR 0.29), and objective response was 41% versus 8%. The FDA has approved nirogacestat for adults with progressing desmoid tumours who require systemic treatment.
Ovarian toxicity
Ovarian dysfunction has been reported with nirogacestat, so fertility and reproductive goals should be discussed before treatment, especially in younger patients.
TKI and chemotherapy
Other systemic approaches remain relevant depending on disease tempo, symptoms, anatomy and previous treatment.
Is radiotherapy needed?
Radiotherapy is not a routine first treatment for most desmoid tumours. It can be considered selectively when active treatment is needed and surgery or systemic therapy is not optimal.
An evidence-based international option does not automatically mean routine access in Ukraine. Registration, procurement and individual access need to be checked at the time of decision. Lack of one drug does not mean surgery is the only alternative: active surveillance, TKI, selected chemotherapy, radiotherapy and local approaches remain part of the modern strategy.
Evidence base
Rare disease needs the right pathway
Desmoid fibromatosis is not a conventional malignant sarcoma and often does not require immediate surgery. In a specialized sarcoma treatment unit, the key is distinguishing active-surveillance situations from those that genuinely need systemic, local or surgical treatment.
Reference-center survival figures from adult STS registries are not directly extrapolated to DFSP or desmoid fibromatosis; disease-specific guidance is more appropriate here.